
Nuclear cataract
The central part of the natural lensOften develops gradually and may first change distance or reading power.
From confirming whether a cataract is causing your symptoms to choosing an intraocular lens and planning recovery, JEWCC brings every decision into one clear, consultant-led pathway.
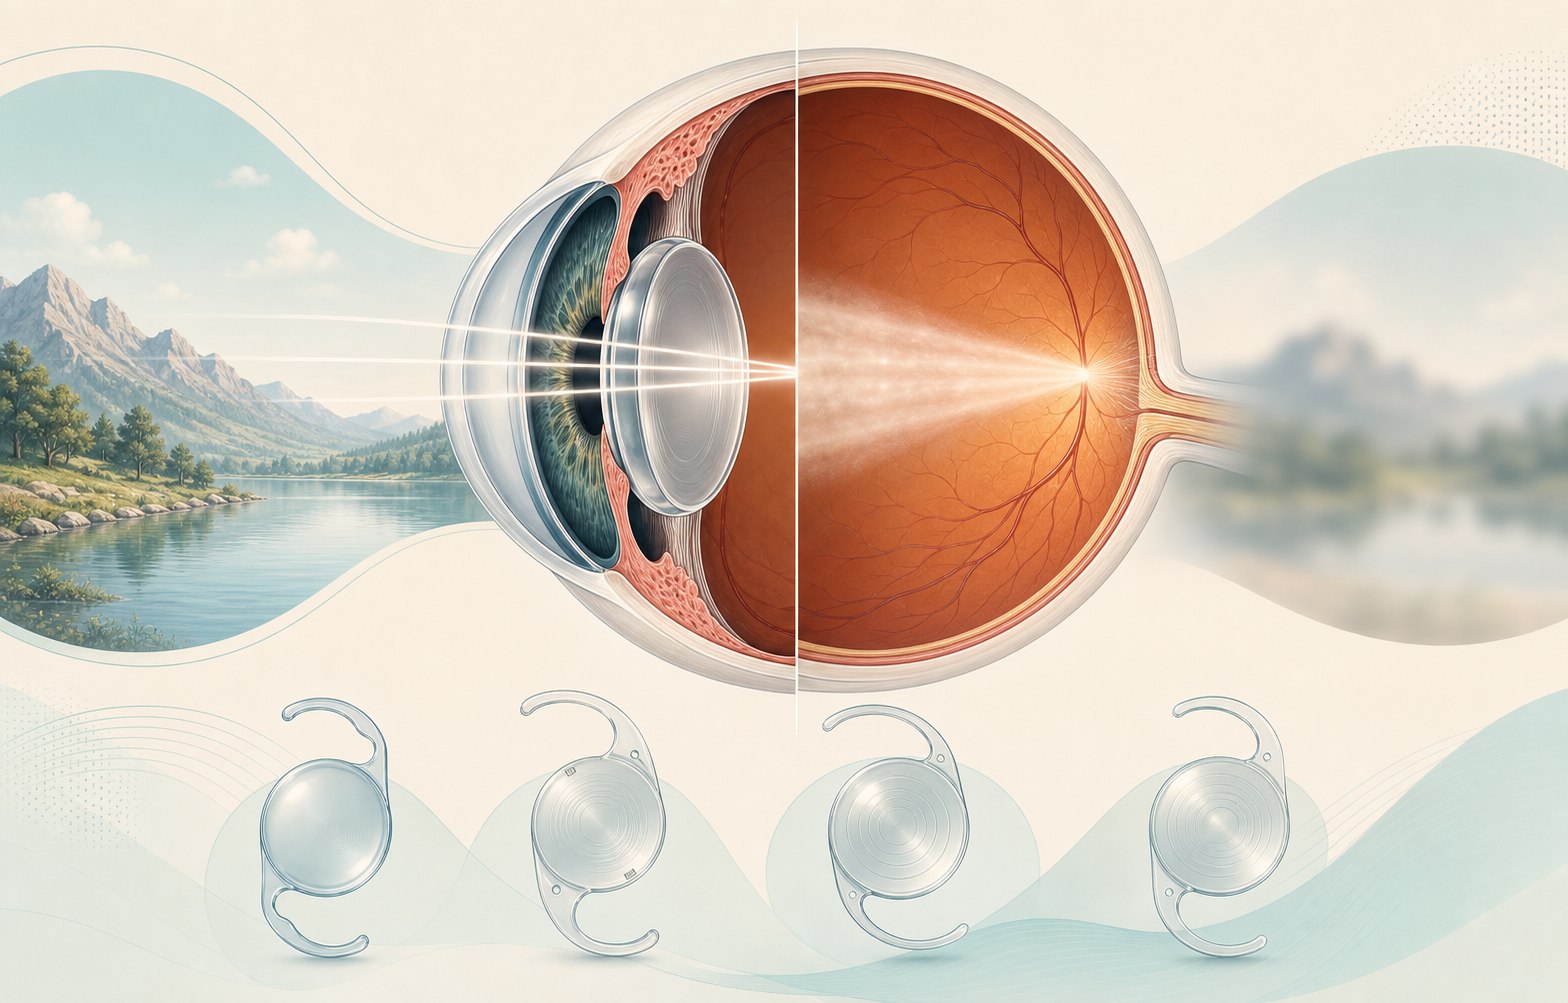
A healthy natural lens helps focus light sharply on the retina. With cataract, proteins within that lens change and cloud it, so light becomes scattered and vision can look hazy, dim or washed out.
Cataracts usually develop gradually with age, but diabetes, steroid medicines, smoking, UV exposure, injury and previous eye surgery can increase risk. Cataract cannot spread from one eye to the other, although both eyes may develop it at different rates.
Often develops gradually and may first change distance or reading power.
Can scatter light and make glare, contrast and night vision more difficult.
May affect reading and bright-light vision and can progress more quickly.
The most common reason the natural lens becomes cloudy.
Can increase the likelihood of cataract and may affect surgical planning.
Long-term use can increase risk; never stop prescribed medicine without medical advice.
Long-term sunlight exposure is associated with cataract risk.
Smoking is associated with a higher risk of cataract.
Trauma or previous eye procedures can contribute to cataract formation.
Surgery is usually considered when cataract-related vision interferes with reading, driving, work, mobility or other daily activities—or when the cataract prevents your doctor from examining or treating the back of the eye.
Early cataract symptoms may temporarily improve with brighter lighting, anti-glare measures or an updated spectacle prescription. These do not remove the cataract. A detailed examination helps separate cataract symptoms from retina, cornea, glaucoma or other eye conditions.
Cataract information is often passed down through family experience. Some of it reflects older surgical practice, while other statements leave out important exceptions. These explanations give a safer starting point for a discussion with your eye surgeon.
A cataract is clouding within the eye’s natural crystalline lens. The front surface of the eye can look completely normal even when the lens inside has become cloudy.
Surgery does not usually require a cataract to reach a fixed maturity. Timing is based on symptoms, daily function, examination findings and whether the likely benefit outweighs the individual risk.
The removed natural lens cannot develop another cataract. The thin capsule holding the IOL can later become cloudy—called posterior capsule opacification—and this is commonly treated with a short laser procedure when needed.
Cataract surgery is commonly performed as a day procedure, so many patients return home after a monitored recovery. The care setting and length of stay still depend on the patient, anaesthesia and procedure.
Age-related cataract is the most common type, but cataract can also be associated with diabetes, steroid medicines, injury, previous eye surgery or conditions present from birth.
No established eye drop, medicine or supplement removes an existing cataract. Lighting changes and updated glasses may help early symptoms, while surgery removes the cloudy lens when treatment is appropriate.
Cataracts in both eyes are often operated on separately so healing and vision can be reviewed. Same-day bilateral surgery may be considered in selected settings, but it is not automatically appropriate for every patient.
Dr. Anand Jaypuriya assesses the cataract alongside the rest of the eye, so the plan reflects more than lens clouding alone.
Eye measurements, corneal astigmatism and your preferred visual target guide the power and type of lens considered.
We compare likely range of vision, glasses use, night-vision trade-offs, suitability and financial considerations without presenting one lens as best for everyone.
Selected eye surgeries are performed at the Nallasopara East eye centre, with planned preparation and follow-up across the JEWCC network.
The exact technique, anaesthesia and recovery plan are personalised. This overview explains the common sequence without suggesting that every cataract operation is identical.
The pupil is dilated, the eye area is cleaned and anaesthesia is given—often with numbing drops, sometimes with another technique chosen for the patient. A sterile covering helps protect the surgical field.
The surgeon works through a small opening and removes the cataract from its thin capsule. The exact method can vary; ultrasound-assisted removal is commonly used, while other techniques may be selected for particular eyes.
A foldable intraocular lens is inserted and positioned inside the remaining lens capsule. The IOL power and design have already been planned from the eye measurements and counselling discussion.
The surgeon checks the IOL position and the small wounds. Many modern incisions seal without stitches, although this depends on the operation. After a short monitored recovery, many patients go home the same day with written instructions.
Cataract surgery is still surgery and has potential risks. Your surgeon should explain the planned method, expected benefit, alternatives and case-specific risks before consent.
An IOL replaces the clouded natural lens. The right design is selected only after measurements and an examination of the cornea, retina and optic nerve. Toric correction can exist within more than one focus-range category.
The target can be discussed for each eye; no target guarantees freedom from glasses.
Detailed lens guidePerformance varies by lens design and the health of the eye.
Detailed lens guideToric describes astigmatism correction—not the number of focus distances.
Detailed lens guideHalos, glare or reduced contrast can occur, particularly in low light.
Detailed lens guideRange and night-vision effects depend on the specific design and the individual eye.
Detailed lens guideThese comparisons are general. Availability, suitability and expected performance depend on the individual eye and the specific lens model. No IOL guarantees complete freedom from glasses.
Vision, cataract, cornea, eye pressure, retina and any conditions that could affect the outcome are evaluated.
Measurements of the eye help calculate IOL power. Astigmatism, lifestyle and spectacle goals are discussed.
The cloudy natural lens is removed and an artificial intraocular lens is placed. Your surgeon explains the planned technique and anaesthesia.
Prescribed drops, eye protection and scheduled reviews support healing. Advice is personalised to your procedure and eye health.
Follow the exact drop and activity instructions given by your surgeon. Seek urgent medical advice for worsening vision, severe or persistent pain, marked redness, flashes, or a sudden increase in floaters.
Read the aftercare guideJEWCC is empanelled with 40+ insurers and TPAs for eligible treatments. Cataract coverage commonly depends on medical necessity, waiting periods, package limits, room or procedure terms, the approved IOL category and pre-authorisation.
Important: a cashless card does not automatically mean every lens upgrade is fully covered. The insurer or TPA makes the final decision.

Dr. Anand Jaypuriya guides assessment, lens counselling, surgical planning and follow-up, with the goal of matching safe clinical care to the way you use your vision every day.
View doctor profile →Consultation and follow-up may be coordinated across the JEWCC eye-care network. The team will confirm the centre appropriate for your examination, measurements, surgery and review.
Jaypuriya Eye Care Centre
This hub now supports focused location, lens, cost and recovery pages without repeating the entire cataract explanation.
Not usually. The timing is based mainly on how vision affects daily life, what the examination shows and whether the cataract is limiting treatment of another eye condition. Your surgeon will discuss the benefits and risks for your eye.
No established eye drop or medicine removes a cataract. Brighter light or an updated spectacle prescription may help early symptoms, but surgery is the treatment that removes the cloudy natural lens.
There is no single best lens for everyone. The choice depends on eye health, corneal astigmatism, retinal and optic-nerve health, visual priorities, night-driving needs, willingness to use glasses and budget or insurance terms.
Premium lenses can reduce spectacle dependence in suitable eyes, but no IOL can guarantee that glasses will never be needed. Some designs can also cause halos, glare or reduced contrast, especially early on or in low light.
Many policies cover medically indicated cataract surgery within approved package and lens limits. Cashless treatment depends on policy eligibility, waiting periods, exclusions, insurer or TPA authorization and the selected lens. The JEWCC team can help check documentation, but final approval comes from the insurer or TPA.
Consultations are available across the JEWCC eye-care network. Selected eye surgeries are performed at the Nallasopara East centre, which has the dedicated eye operation theatre. The team will confirm the appropriate location for your case.